CheckEmoji Community · the emoji forum
🏠 Home 🆕 What's new ❓ Unanswered 🔥 Popular 📡 RSS Members 👥 0 online log in · register
Home › Nicholas Myers › Posts

Posts by Nicholas Myers

1304 posts shown.

slystag4 said:Thanks a lot. Here was the situation: two weeks before this bloodwork, I had a fever, body aches, nausea, and intense joint pain. Eight days prior to this liver panel, my levels were extremely high, including a CRP of 17. Around that same time, we ran serology for CMV (IgM negative, IgG positive) and parvovirus (IgM negative, IgG positive). Eight days after the liver tests, everything looked normal again—except for the GGT, which dropped significantly from being three times the limit, and amylase, which hit 118 (normal range goes up to 91).

When should I schedule a follow-up EBV serology test?

Repeat the serology testing 2-3 weeks after the initial test.
Quote : my Name is
bluepilot45 said:Following that second blood draw, my GP decided I had some sort of low-grade inflammation she couldn't quite pin down. Her solution? A prescription for Amoxicillin—1000 mg, twice a day, for seven days.

She also gave me a referral for follow-up blood work ten days after finishing the antibiotics, though that ten-day mark hasn't actually hit yet.

Thanks and cheers to everyone!

To whom it may concern,

Follow your doctor's instructions. Your results should return to normal soon.

Quote : my Name is
Betty Nelson71 said:Went to the doctor yesterday about some health issues. They ran a quick urine test using those reagent strips, and the nurse mentioned there was just "one little line" for protein. When I asked for clarification, the doctor brushed it off, saying everything looks perfectly fine and it’s a normal result. Still, that comment from the nurse stuck with me. It felt off. Naturally, I did what anyone would do and hopped on Google, and now I'm an absolute wreck. Every search result says a positive protein reading is a red flag for kidney or heart disease. Now I'm spiraling. I have follow-up blood work and more detailed testing scheduled for tomorrow.
I’m starting to panic a little...
__________________

To whom it may concern,

To offer any meaningful commentary, we’d need to see the rest of the urinalysis results—specifically the sediment analysis. It’s also worth questioning if the sample itself was clean; you can't rule out contamination if vaginal discharge mixed with the urine during collection. Given those variables, repeating the test alongside some supplemental screenings would be the prudent move.

Megan Hayes40 said:To whom it may concern,

I just got my blood work back. It was just a routine checkup I decided to schedule myself, since I haven't felt the need to see a doctor in a few years.

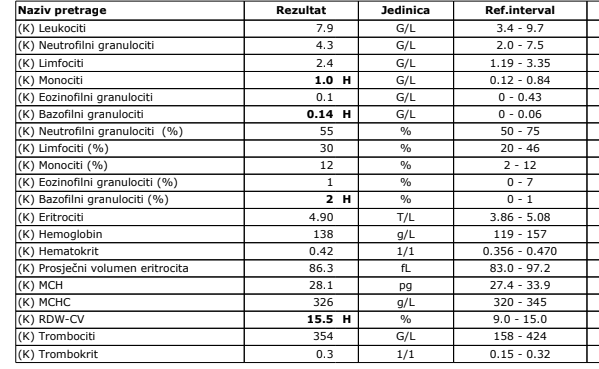
image

https://ibb.co/Ypbwjg4

Is a high basophil count cause for concern if you're young, healthy, at a normal weight, a non-smoker, and generally living a balanced lifestyle? I have a consultation scheduled with my primary care physician next week, but we all know what happens when you type "basophilia" into Google. 🤦

So, I might be overreacting just a little bit.

Thanks in advance!

To whom it may concern,

I don't see any reason to get worked up over these results. We only talk about true basophilia when the count exceeds 0.2x10*9/L. Those serious diagnoses you’re mentioning usually involve much higher numbers—starting around 0.5x10*9/L and up. Your report shows only a slight elevation in basophils and monocytes. It looks like a reactive, transient response. In my view, there's no reason to panic right now.

slystag4 said:Can someone please help me make sense of this?

EBV VCA IgM-negative
EBV VCA IgG-positive
EBV EA IgG-borderline
EBNA IgG-negative

What does this pattern indicate?

Hi there,

It isn't possible to provide a definitive interpretation from these numbers alone. This could represent an active EBV infection currently underway, or simply a past infection that has already run its course. Typically, doctors look at how these results align with actual symptoms—like fatigue or fever—alongside other lab work (for instance, a CBC or liver function panel) before deciding whether to re-run the serology.
Quote : my Name is
Emily Ortiz27 said:Much appreciated, Elgato.
Unfortunately, we can't get you in for an exam right now. We'll only consider a follow-up if things take a turn for the worse.

Why? His pediatrician won't even see him?

I’m also concerned about those low neutrophil counts, elevated eosinophils, and the constant presence of atypical lymphocytes.
If this finding remains constant, should we just accept it as the child's baseline?

The results look quite decent, even for a perfectly healthy kid—aside from the eosinophilia, which just points to an allergic reaction in your child. Neutrophils are essentially normal, and that 3% of atypical lymphocytes isn't really anything to worry about either. Given the circumstances, I’d call this more than satisfactory.
Megan Jones27 said:Thyroid hormones..
https://ibb.co/SR41jF8

Would checking PTH be appropriate here?

Sent from my Samsung Galaxy using Reddit

I'm inclined to agree with what the colleague mentioned regarding Coca-Cola earlier. There isn't a clinical indication to test PTH right now.

Emily Ortiz27 said:A kid with lymphadenitis—regular follow-up, but there's no one available to re-examine him. Any thoughts? We haven't managed to get a cytological smear yet. I'll post an update if anything looks off.

(image)[/IMG]

(image)[/IMG]

(image)[/IMG]

The results look good, as you can see, but they aren't a substitute for a physical exam.
Quote : my Name is
bluepilot45 said:To whom it may concern,

Thanks for the response. I went back for a follow-up four weeks after the first set of tests, and while those same parameters are still elevated, they are showing a slight downward trend:

White blood cell count: 11.1 (normal range 3.4-9.7). On the first blood draw, it was 11.3.
Lymphocytes: 3.41 (Range: 1.19-3.35) — compared to the initial blood draw at 4.50.

Now I’ve got elevated neutrophil granulocytes: 6.85 (range 2.06-6.49). On the first blood draw, they were fine at 5.86.

The MPV hasn't been repeated.

I also dug up some results from about a year ago, and back then, everything was perfectly within the normal range.

One detail I missed in my first post: I had blood work done because of these sudden, intense bouts of vertigo. The labs ruled out anemia and thyroid issues, and my carotid artery scans came back clean. An eye exam was fine too, though the X-ray of my cervical spine wasn't exactly great news. Ultimately, an ENT specialist—even without running a full vestibular test—concluded it’s just Benign Paroxysmal Positional Vertigo caused by those tiny calcium carbonate crystals getting dislodged. I was prescribed Betaserc, 24 mg twice a day. I've been on it for about ten days now, and honestly, it’s making a real difference.

My biggest concern right now is whether I even have the right diagnosis. Looking at my blood work, I’m starting to wonder if this is actually BPPV, or if we're looking at some kind of inner ear infection or something else entirely. Should I be pushing for more testing? (That's just my layperson's take.) 😁)

Thanks in advance for the response.

To whom it may concern,

A diagnosis of benign paroxysmal positional vertigo is clinical. If the physical exam aligns with that finding, there’s no need for further testing. It’s straightforward.

Regarding the blood work, it would be best if you could provide the full panel. It’s also worth repeating both the CRP and ESR tests alongside the complete blood count.

Quote : my Name is
Emily Ortiz27 said:Hello.
An eight-year-old girl underwent thyroid testing after some slight swelling was noticed around her neck.

The results are in:
FT3 5.41 (Range: 5.1 – 7.4)
FT4 levels sitting at 11.12 (range: 11.1–18.1).
TSH at 50.063 (Normal range: 0.67–4.16).

I’ll provide my response over on the Pediatric Health PDF, since that's where you posted the inquiry.

Quote : my Name is
Grace Kelly39 said:TSH at 1.117.
FT4 at 13.9.
Anti-UN Anti-UN 337,3

Can anyone break this down for me? Looking for some forum-style interpretation here. 😁
Last time, my triglyceride levels were quite high—actually higher than they are now—but I didn't follow up with any more testing. This time around, I’m planning to see an endocrinologist. Thanks in advance for the input. 🙂

Hello,

As you can see from your results, you are euthyroid. Your thyroid hormone levels are within the normal range, so there is no clinical indication for hormone replacement therapy at this stage. However, you do have elevated thyroglobulin antibodies. Since thyroglobulin is a protein produced by the thyroid cells to help manufacture hormones, having these antibodies present can sometimes point toward the development of an autoimmune thyroid condition. That said, thyroglobulin antibodies aren't quite as specific as anti-UN markers, meaning their presence alone isn't enough to confirm an autoimmune disease. I'd suggest scheduling a follow-up with an endocrinologist. Depending on whether you've had one recently, an ultrasound might be worth considering, and you should work with them to establish a schedule for monitoring your hormone levels moving forward.
restlesscobra13 said:Hello,

Thank you for getting back to me and for taking the time.
I had blood work done on February 23, 2021. I'm attaching links to the results here. (CBC, sedimentation, biochemistry, CRP, immunoglobulins, anti-CCP, RF, thyroid hormones, ANA, covid)
https://ibb.co/jJYS7b5
https://ibb.co/L534Xdk
https://ibb.co/XLW0098
The abnormalities present are:
MPV 13.1 ( ASO 675 ( anti-TPO 65.32 ( I also had a peripheral blood smear performed.
Neutrophils 67 (44-72)
Lymphocytes 22 (20-46)
Monocytes 10 (2-12)
Eosinophils 1 (0-7)
Red cells, granulocytes, and platelets look normal morphologically. No immature hematopoietic cells.
Does an ANA titer count as positive or negative if the threshold is Any idea where I should go from here?

In your case, the ANA is negative. Given these numbers, it’s unlikely you're dealing with an active systemic rheumatic disease right now. It's a bit like looking at a scattered puzzle; I'll need to sit down with this when I have more time to see if anything else sticks out. I noticed you mentioned joint swelling earlier—has that ever been clinically confirmed? Specifically, have you had an ultrasound or an X-ray on those swollen joints, and if so, what did they show?
Hopefully, I've finally cleared out the backlog that piled up over the last few weeks.
bluepilot45 said:Hi there,

I’m 41. No chronic issues, no medications, and I’m a moderate smoker (about 10 cigarettes a day).

My recent blood work has me a bit uneasy because both my white blood cell count and lymphocyte count are elevated:

WBC 11.3 (3.4-9.7)
MPV 11.1 (6.8-10.4)
Lymphocytes 4.50 (1.19-3.35)
Glucose 6.5 (4.4-6.4)

Everything else looks fine—CBC, differential, urea, creatinine, eGFR, bilirubin, AST, ALT, GGT, potassium, sodium, iron, CRP, lipids, TSH.

My doctor asked if I'd had any significant colds lately, but I haven't. Should I be concerned about these numbers?

Thanks.

Hello,

In the middle of the road here—mild leukocytosis with lymphocytosis. You see results like this in smokers sometimes, but you really need to compare them against your previous labs and have a clinical exam. I’d suggest repeating the test in 3-4 weeks just to track the trend.

Kenneth Rodriguez15 said:Hi,

I'm in my early thirties and have been doing annual physicals through my supplemental insurance policy for years.
Everything comes back normal, except for:

Alpha-amylase: serum 112 (23-91), urine 447 (
Back in November 2019, the results were very similar: serum alpha-amylase 112, NSE: 18.4.
However, they normalized after a month (December 2019): alpha-amylase 80, NSE: 13.5.

I plan to follow up with my doctor, but since my policy covers specialist consultations, I'm trying to decide the smartest way to handle this.
I don't have any symptoms.

Hello,

By all accounts, we're looking at minor deviations that have been fluctuating for over a year now. It seems highly likely there's no underlying cause and nothing serious happening, but since there is a slight deviation, the bare minimum is a medical consultation. Internal medicine specialists covered by those types of insurance plans usually handle these check-ups and can advise you on the next steps.
Jessica White95 said:Questions: if things take a turn for the worse, what kind of therapy would help? Xorimax wasn't exactly a miracle worker, so would Zithromax do the trick? Is taking too many antibiotics in such a short window actually dangerous? I haven't had any side effects yet, but the thought of starting a third antibiotic is nerve-wracking.

Ma'am,

I haven't been able to check in until now. If you're still struggling, a chest X-ray is necessary, and you should consider serology for atypical pathogens—think Mycoplasma, Chlamydia, or perhaps others depending on the clinical history, like Coxiella burnetii.

There’s no reason to fear Azithromycin (Zithromax), though whether it's indicated in your specific case is something I can't determine with certainty over an online forum. One thing is clear: it would have been my choice before Xorimax, especially since Klavocin failed to yield results.

Emily Ortiz27 said:Hello, I need some help interpreting my results today.
My hormone levels were tested due to irregular menstrual cycles. My cycle lasts about 23-27 days, with bleeding lasting 7-8 days—usually a long period of light spotting followed by two days of heavy bleeding with significant clotting.
I experience painful ovulation, and occasionally pain during intercourse or certain positions while exercising.
The ultrasound for my uterus and ovaries came back normal.

Hormone panel from day 4 of the cycle:
Please let me know how to interpret these hormone levels taken on day 4 of the menstrual cycle:

LH (s) 3.98
FSH (s) 10.95
Prolactin (s) 209
Estradiol (s) 98.75
Testosterone (s) 1.47
Tested via ECLIA method, Roche Cobas E601 (E411)

It looks to me like the results fall within the reference range for the follicular phase, though they sit on the lower end.

Ma'am,

Please include the units of measurement and the reference ranges provided, as those vary from one lab to another. Based on what you've sent, however, there don't seem to be any major deviations.

Has endometriosis been considered as a potential cause for your symptoms?
restlesscobra13 said:To whom it may concern,

I’ve been dealing with painful joints, bones, and muscles for two months now. It started off minor, but it's steadily getting worse. Some of my joints are swollen, and even some muscle tissue. On top of that, I have reactive lymph nodes in my neck, armpits, and groin (confirmed via ultrasound). My abdominal ultrasound came back clear.
I had Strep A in my throat maybe four or five times—possibly more—and now I'm testing positive for Group B Strep vaginally.

Back in December, my peripheral blood smear was normal.
In early January, I had a CBC, ESR, CRP, and ASO titer checked. Monocytes were elevated (12.2, limit is 12), MPV was high (12.5, normal is under 10.4), and ASO was 695 (normal is under 200).

My immunologist ordered RF, CCP, and HLA-A, B, and DR locus testing. My radiologist even suggested a lymph node biopsy to get a better look at what's going on, along with serology, though I'm not sure which specific tests are needed.

I am considering ordering a CBC, peripheral blood smear, liver enzymes, ALP, LDH, CRP, ASO, and testing for EBV and Cat Scratch Disease.
If anyone has further recommendations for lab work, I would appreciate it.

Thank you.

Ma'am,

Regarding serology to rule out infectious causes for enlarged lymph nodes: typically, alongside EBV and Bartonella (Cat Scratch Disease), one should also check for CMV and toxoplasmosis. HIV should also be considered. Other pathogens aren't usually tested routinely unless your medical history specifically points toward them.

As for rheumatological testing, there are other options, but we really ought to wait for the current results to come in before deciding on those.
Ronald Kern78 said:Hello,

I’ve completed the requested tests. Here are the links to the results:
CBC - https://app.box.com/s/fwp3y4gbids9s7tgzyqoxvja1u3hmu5c
Liver enzymes - https://app.box.com/s/gaj5r5kyev5yvxvhs0axmw2i99k3r00u
CRP - https://app.box.com/s/p26bk9066frhu9i2funrgh3u4pplcazi
LDH and CK - https://app.box.com/s/5wz4f2cvni8t23tysg2m8uaxcydfuebs

Essentially, my lymphocytes have dropped and are nearly within the normal range - 3.4 (1.19-3.35)
The ESR is slightly lower, but from what I've read, that shouldn't be an issue.
Everything else falls within the standard reference ranges.

The only elevation is in the liver enzymes, specifically ALT at 64 (normal is 12-48).
A week ago, following my doctor's suggestion regarding suspected gastro reflux, I started taking ZOPRAX (20 mg pantoprazole). Is it possible this medication is causing the elevated levels? (The patient information leaflet notes that if liver enzymes increase, usage should be discontinued)

In your opinion, do I need more testing, or would it be sufficient to just recheck the liver enzymes after some time?
On a side note, I feel fine right now; it feels like the lymph nodes in my neck have shrunk.

Thanks for the guidance and explanations!

Hello,

Given your history of lymphocytosis, the enlarged lymph nodes in your neck (though I am unsure if they are still present), and the altered liver function tests, an infectious cause—specifically infectious mononucleosis syndrome—seems likely. I stand by my previous assessment: we really need to identify which specific infection we are dealing with. It is a positive sign that the lab work is improving. You can recheck the liver panel in two weeks to a month.
Linda Gray said:Repeating my question here, if anyone actually knows🤔

Hello,

To make sense of these numbers, I’d need to know which specific units were used for the insulin measurement. Even without that detail, though, the insulin levels look elevated—particularly at the 120-minute mark.

Strictly speaking, based on these results, there isn't insulin resistance present at the time of the test. An HOMA index of 1.0 is essentially textbook perfect, suggesting good insulin sensitivity. Where things get a bit inconsistent is the combination of those relatively high insulin values alongside the somewhat low activity from the pancreatic beta cells responsible for producing it.

Depending on why this testing was ordered in the first place, it might be worth repeating the process down the road.
Ronald Kern78 said:To whom it may concern,

Is it possible that my absolute lymphocytosis and swollen lymph nodes are a result of the toothache I've been dealing with over the last few weeks? I recently had a small cavity filled, but about a week later, the pain started. It isn't constant—just hits every couple of days.

Best regards,

To whom it may concern,

Swollen lymph nodes in the neck can certainly be linked to odontogenic infections—essentially, dental issues. However, lymphocytosis typically doesn't fit that picture. Bacterial infections generally don't trigger lymphocytosis (flu is an exception, but that’s a different matter entirely).

In any case, you need to investigate the cause of both the rising absolute lymphocytosis and those enlarged cervical lymph nodes.
Peter White80 said:Dear sir,

Thank you so much for such a thorough response.

Unfortunately, I've already undergone extensive testing and everything was relatively orderly. The only outliers were: GERD/LPR plus esophageal issues, bouts of constipation (though my colonoscopy was clear), some vestibular issues, slight thickening of the carotid arteries in the neck, and systolic hypertension. Key findings to note: CRP 18.0 mg/L, ASO 243 IU/mL, triglycerides at 3.3 mmol/L. Also, a 4 mm cyst on the upper left third of my thyroid lobe.

I'm not sure if this matters, but I am extremely sensitive to sunlight—even staying in the shade during summer causes a rash on my back.

In your opinion, should I pursue further testing, or simply focus on a healthy lifestyle and hope that no actual disease develops?

Thanks for getting back to me.

Best regards,

Dear sir,

Given the collection of data and the various specialist opinions you've gathered, it makes sense to consult a rheumatologist or a clinical immunologist. You need someone to synthesize all these disparate pieces into a single clinical picture.

To be blunt, I doubt you'll walk away with a definitive diagnosis at this stage.
Emily Ortiz27 said:I don't think we have a pediatric infectious disease specialist here in San Francisco. I assume we'd need a referral to go to the Mayo Clinic in Washington, D.C.?

No, there shouldn't be any need to travel to Washington, D.C. just for that. You can handle everything right here in San Francisco.

The child doesn't meet the criteria for AST-O titer testing.
Bonus question: given that borderline TSH value, should we monitor the thyroid after a while? There's a history of thyroid issues in the family—my grandmother and uncle both had them, and I personally dealt with thyroid fluctuations after every pregnancy that eventually settled on their own.

In my view, setting the upper limit for TSH at 3.35 mIU/L for a child this age is overly restrictive. I wouldn't classify a TSH at the top end of the normal range as a cause for alarm. As for whether monitoring is necessary or how frequently it should happen, that’s a conversation for the primary pediatrician. They'll determine if there's a clinical indication for follow-up and set the appropriate intervals.
Ronald Kern78 said:Hi, following my second blood panel (taken 15 days later), here are the shifts:

- LYMPHOCYTES 45.9% (ref range 20-46)
and they are at 5.0 10^9/L (ref 1.19 - 3.35)
- WHITE BLOOD CELL COUNT 11 (ref 3.4 - 9.7)
- EOSINOPHILS 0.5 10^9/L (up to 0.43)

- NEUTROPHILS - have dropped to 43.5% (ref 44-72)

The gastroenterologist claimed this blood work is normal (?) and after an ultrasound of my abdomen and neck, concluded all organs/thyroid look fine. He did find two enlarged reactive lymph nodes in my neck, measuring 35 mm. In his view, no further follow-up is required.

However, I still have this "lump in my throat" sensation and a dull ache where those lymph nodes are located on my neck and under my jaw. I've also been struggling with sleep lately (waking up after 3-4 hours and being unable to drift back off). In your opinion, is it wise to seek a third opinion? And is this blood work really "normal" as the gastroenterologist suggests?

Thanks in advance 😁.

Hello,

You should pursue further testing. While your differential white cell percentages look standard, you have absolute lymphocytosis paired with enlarged cervical lymph nodes labeled as reactive. As a starting point, it seems reasonable to order a peripheral blood smear, ESR, CRP, liver function tests, CK, LDH, and serology for CMV and EBV. Depending on clinical indications—based on a detailed history (including sexual history) and physical exam—further screening for other infectious agents may be necessary.
Emily Ortiz27 said:A 13-year-old was sent for lab work due to a low-grade fever lasting just over a week. No other symptoms reported.
Normal build, appetite, bowel movements, and urination patterns.
COVID test negative.

Blood counts look fine.
Urinalysis: physical and chemical properties are normal.
In the urine sediment, there's an elevated red blood cell count (8 vs. ref range 0-2), some mucus, some spermatozoa, and quite a few bacteria).

Biochemistry:
Glucose 5.3 (3.9-5.9)
Urea 5.0 (2.7-6.8)
Creatinine 66 (25-42)
Total Bilirubin 13 (6-24)
AST 19 (11-38)
ALT 10 (10-33)
GGT 12 (10-27)
CRP 0.3 (0.1-2.8)

TSH 3.35 (0.68-3.35)

The doctor ordered a repeat urinalysis.

The kid stays moderately active, but hasn't trained in the last 8 days because of the fever. He's mostly stayed indoors—training intensity has been lower than usual anyway due to recent restrictions.
Tests were done in the morning, fasting.

Hello,

The child should probably have a chest X-ray. It would also be wise to check ESR, CK, LDH, electrolytes, and run a urine culture. Beyond that, testing for atypical infectious agents that might present this way—specifically Mycoplasma pneumoniae or certain viruses—would be prudent. If you haven't already, I’d suggest contacting the Mayo Clinic.
Peter White80 said:Good day, everyone.

I had blood drawn to analyze my MHC system because I've been dealing with a persistent low-grade fever since May 2020. My temperature regularly hits 99.5°F. I'm also dealing with heat sensations and sweating. Vitamin D levels are between 16-18. TSH is normal.

Here are the results: (the numbers are listed in two sets, separated by a vertical bar)

HLA-A*
02 | - (possible homozygosity)

HLA-B*
08 | 41

HLA-C*
NT | NT (not typed)

HLA-DRB1*
03 | 11

HLA-DqB1*
02 | 03

I would be very grateful if someone could look over these results!

Best regards!

Sir,

I hope you have already undergone a thorough medical evaluation. This shouldn't be one of the first complex lab tests performed, because based on your clinical history, this HLA typing won't provide the clarity you might expect.

I won't delve into the specifics of why through an online forum.

From the HLA typing, we can see a genetic predisposition toward systemic autoimmune diseases. Specifically, there is an increased risk for systemic lupus erythematosus (primarily HLA-DRB1*03, which increases the risk by two to three times compared to the general population), juvenile dermatomyositis (you also carry HLA-B8, which is more prevalent in patients with inflammatory muscle diseases within overlap syndromes), and unfortunately, HLA-DRB1*03 could also signal an elevated risk for juvenile systemic scleroderma (further complicated by your HLA-DRB1*11, which is linked to systemic scleroderma risk), as well as a higher risk for Sjogren's Syndrome. Additionally, HLA-DRB1*03 is associated with a slightly increased risk for multiple sclerosis, though the margin is quite small.

You are just short of the threshold for an extremely high risk of systemic lupus erythematosus. If you possessed the HLA typing combination of A1-B8-DR3 (whereas you have A2-B8-DR3), your lifetime risk of developing that disease would be ten times higher, which would also significantly spike the risk for other systemic autoimmune conditions.

Furthermore, you have an increased genetic predisposition for autoimmune thyroid diseases, Type 1 diabetes, and celiac disease (with the caveat that the typing was not performed with enough "granularity").

None of these conditions are a certainty; you may never develop any of them. We are strictly discussing predispositions.

I should also note that my entire response is qualified by the fact that the typing wasn't done with enough detail—specifically at a four-digit resolution. In your case, it was done at a two-digit resolution, often referred to as low-resolution typing.

I hope my opening sentence makes sense: this specific test creates more questions than answers, and it certainly shouldn't be used as the starting point for evaluating a patient with vague symptoms.

Good luck.
Emily Ortiz27 said:Could you elaborate on neutrophil granules? Also, these rouleaux formations pop up constantly in my smears. I’ve read they can be an artifact of poor sample prep, but at our lab, it feels like we almost always mess up the preparation. 🤔

The results are more than satisfactory. Prominent granules in neutrophils don't point to anything specific on their own. If we were seeing distinct toxic granules, that would suggest an active infection—essentially the neutrophils working overtime to devour pathogens. As for the rouleaux formation, while it can be an artifact, in this context, it's likely tied to the underlying condition and the composition of serum proteins. Children with ALS or similar spectrum disorders frequently present with findings just like yours.
Alex Morales3 said:Hi everyone. I’ve come down with a sore throat that feels like it’s morphed into a sinus infection. My ears are completely plugged, and there’s this constant feeling of mucus in my throat, though there isn't any actual pain. My primary care physician sent me for a sinus scan, which came back clear. My blood work is mostly normal, too, with only a few outliers:

RBC: 5.88 (Normal range: 4.34 - 5.72)
Iron levels: 8.8 (Ref range: 11–32).
CRP at 7.5. Normal range is 0 to 5. Inflammation is present.
Neutrophils at 41.7 (Normal range: 44–72). Slightly under the mark.

Thoughts? She’s claiming it’s just a viral thing, but my ears are still completely plugged. 😢

I’m with your doctor on this one. Right now, it looks like a typical viral infection. I’d suggest holding off on checking your iron levels until this clears up; testing while you're fighting an infection isn't exactly reliable.