CheckEmoji Community · the emoji forum
🏠 Home 🆕 What's new ❓ Unanswered 🔥 Popular 📡 RSS Members 👥 0 online log in · register
Home › Lifestyle › Health › Lab results - looking for opinions [PLEASE READ 1ST POST]

Lab results - looking for opinions [PLEASE READ 1ST POST]

Started by vividsailor7 · · 👁 22 views · 3.9K replies

📡 Subscribe to replies

Participants vividsailor7redcrane22Sandra Rivera37swiftbear86melloworca6Dana Martin87ironskipper80mellowgardener15goldenmarlin6analogbison13Nicholas Myersstormygardener34Roger RodriguezDonna Mitchell3Kenneth Vaughn2Laura Ward98briskseal32Susan Vaughn46Zachary Lewis4driftingmason52rustyheron55Laura Chavez47vividstag24lonecanyon8 …
goldenmoose15 goldenmoose15 Newcomer
1 message
joined Mar 2023
#3781 ·
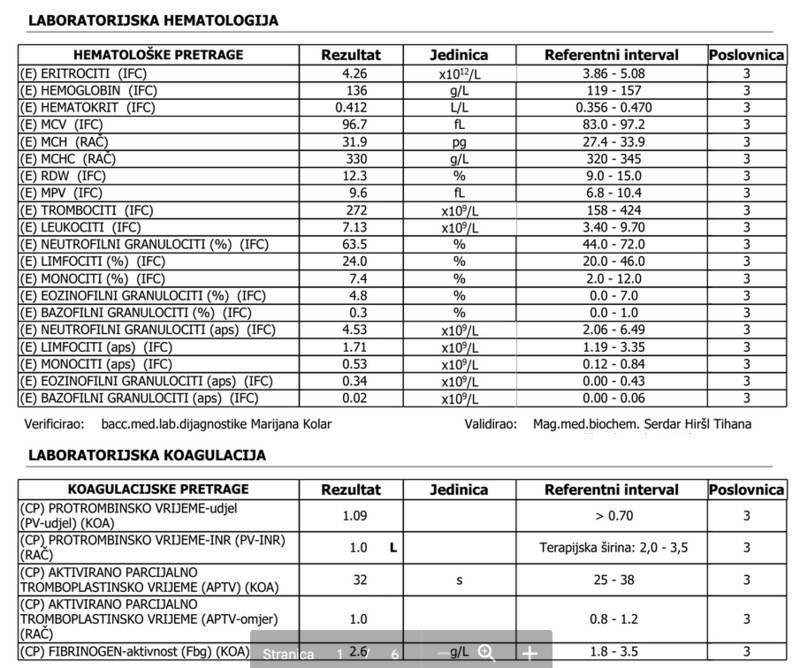
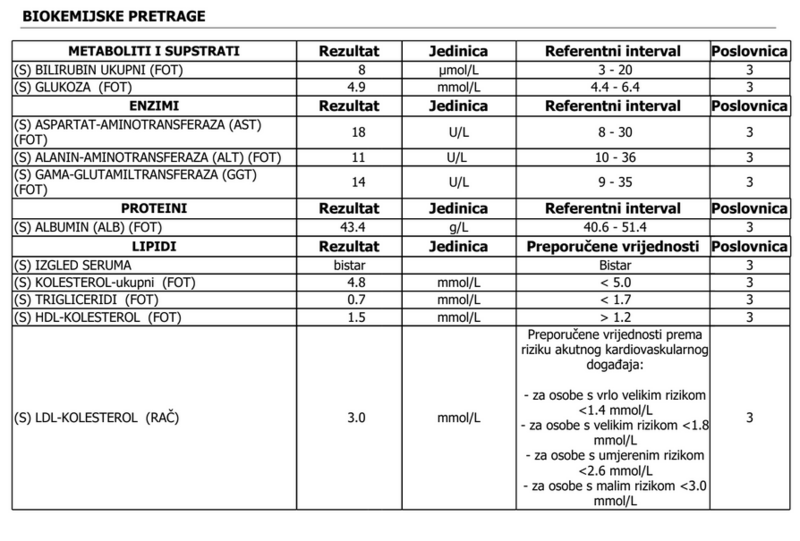
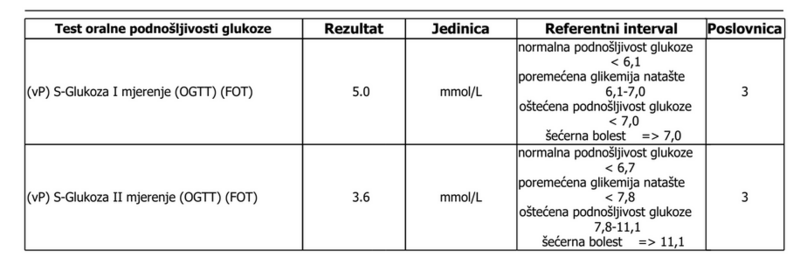
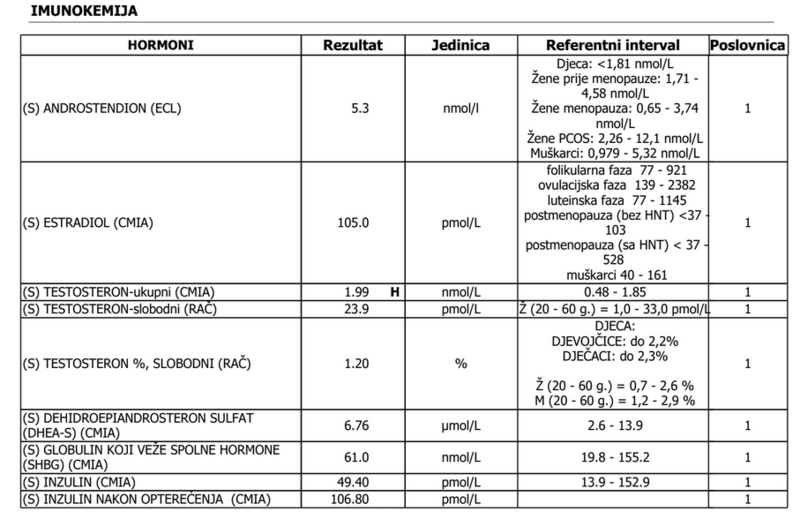
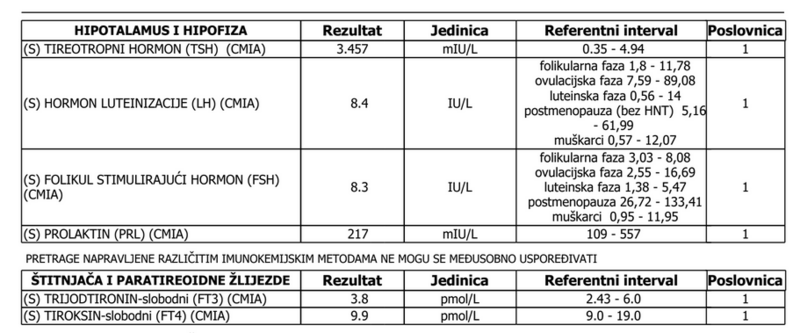
Hello, I’m looking for some help interpreting these results.
They were ordered because there's a suspicion of PCOS and insulin resistance—taken on day five of my cycle—as well as to help determine the best options for birth control.

image

image

image

image

image
Angela Wright Angela Wright Regular
731 messages
joined Feb 2007
#3782 ·
James Harris16 said:https://ibb.co/JxzXm0z

Can someone make sense of these results?

Thanks in advance.

As a layman, here’s how I read this:
It looks like some kind of growth on the lungs (I'm assuming "npl." refers to a neoplasm) and likely enlarged lymph nodes as a result.
A pulmonologist is going to want to run more tests to be sure.

Sent from my Samsung Galaxy using Reddit
Angela Wright Angela Wright Regular
731 messages
joined Feb 2007
#3783 ·
goldenmoose15 said:Hey everyone, I could really use some help interpreting these lab results.

They were ordered because we're looking into potential PCOS and insulin resistance. These were taken on day five of my cycle, and the goal is also to figure out the best contraceptive option for me.

image

image

image

image

image

That elevated testosterone level is likely tied to PCOS, especially since everything else looks normal.
My only real concern is whether this prothrombin time reading might complicate things when choosing a birth control method, given how much they impact clotting.

Sent from my Samsung Galaxy S9 using Reddit
Angela Wright Angela Wright Regular
731 messages
joined Feb 2007
#3784 ·
Robert Davis9 said:Hi there,

For the last six months, I’ve been dealing with these health issues. To be more precise, I think it all kicked off somewhere around April of last year. I had these bouts of dizziness—sometimes when standing up or just moving around, I can't quite pin it down—and my left leg would ache occasionally, from the back of the knee down. Those symptoms still pop up every now and then, along with the vertigo.

Then in November, everything hit the fan: sudden iron-deficiency anemia, high cholesterol, and high triglycerides (which I’ve never dealt with before), plus rapid weight loss. We actually suspect I just lost subcutaneous fat. After that, infectious disease tests came back positive for EBV and CMV (we aren't sure if it was a reactivation or a primary infection). Now, my doctor is suggesting that EBV could potentially cause the loss of subcutaneous tissue and that sharp drop in weight (I lost 6kg in just 3 weeks).
My skin is dry and flaky on my knees and over my heels, my nails are soft with longitudinal lines, and I'm dealing with arthralgia—my knees make crepitus sounds—along with occasional bone pain, though it's always in the exact same spot (my upper arms). Lately, I've also had tingling in the fingers of my left hand. On top of that, I think my tongue looks slightly enlarged; you can see the indentations from my teeth on the front and sides where it fills the gaps from two missing teeth. I've been reading all sorts of stuff online about things like myeloma and amyloidosis, and honestly, the panic is starting to set in.

I've seen a gastroenterologist, an endocrinologist, an immunologist, and several other internists. We've run every test under the sun: CBC is normal except for low hemoglobin and hematocrit; initially, it looked like microcytic anemia (probably because I donated blood three weeks before the first labs), but now it's normocytic. Three abdominal ultrasounds have come back clear, TSH, T3, and T4 are fine, all hormones are okay... colonoscopy was fine, endoscopy was fine, and both CT scans of the abdomen and chest were okay. All ANA/ENA and RF markers are normal too.

Just waiting on an MRI for the small intestine. An echocardiogram was also fine.
I went to a private immunologist who basically told me I'm making up symptoms and diagnosed me with IBD. They have me on Mesalamine without any actual evidence of IBD, Crohn's, or any small intestine issues. My calprotectin levels are normal too...

These are the electrophoresis results from a month ago and the latest CBC after a month of iron supplements—specifically CrossFit. Note that I stopped taking the iron two days before the blood draw. My question is: can iron supplements create a false blood profile, where the numbers look good but the anemia actually persists? Also, how much of an impact can lipemia have on protein electrophoresis? Thanks.

blood test results
Hemoglobin 147
Hct. 0.431
MCv 85.7
Mch. 29.2
Mchc. 341
RDW 13.8
Serum iron 14.3
UIBC 41.8
TIBC 56.1

I think you should get a neurological exam as soon as possible if you haven't already.

Sent from my SM-G960F using Reddit
Robert Davis9 Robert Davis9 Newcomer
8 messages
joined Mar 2023
#3785 ·
Angela Wright said:If you haven't already, I think it would be wise to get a neurological exam done as soon as possible.

Sent from my Samsung Galaxy S9 using Reddit


I have a feeling this might actually be a hematology issue rather than something neurological... I have an appointment with a hematologist at the local clinic this coming Monday, so we'll just have to wait and see how that goes. :/
Angela Wright Angela Wright Regular
731 messages
joined Feb 2007
#3786 ·
Robert Davis9 said:I'm starting to think this might be a hematology issue rather than something neurological... I've got an appointment with a specialist at the local clinic this Monday, so we'll just have to wait and see... :/

Some of the symptoms you're describing are often the very first red flags for MS, so it’s definitely worth ruling that out as soon as possible. That said, CMV could also be the culprit here.

Sent from my Samsung Galaxy using Reddit
Robert Davis9 Robert Davis9 Newcomer
8 messages
joined Mar 2023
#3787 ·
I’m feeling a bit uneasy about the possibility of macroglossia combined with iron-deficiency anemia. I suppose we’ll just have to wait and see what the hematologist suggests for the next steps... personally, my mind keeps drifting toward amyloidosis. I’m really hoping my Easter bunny doesn't show up carrying chemotherapy...
brightgull95 brightgull95 Newcomer
7 messages
joined May 2022
#3788 ·
So, you're saying amyloidosis. Which specific type are we talking about here? There are actually several different kinds, though four of them are the most common. And let's be real—everyone knows that "cherry on top" factor is way more critical than macroglossia. So, cut to the chase: is there a cherry on the cake or not?
Robert Davis9 Robert Davis9 Newcomer
8 messages
joined Mar 2023
#3789 ·
Amyloidosis. It’s one of those things where you don't get the cherry on top, just the crust on the pie.
brightgull95 brightgull95 Newcomer
7 messages
joined May 2022
#3790 ·
Aha. And let me guess—was that advice coming straight from Dr. Google or Dr. Yahoo?
Robert Davis9 Robert Davis9 Newcomer
8 messages
joined Mar 2023
#3791 ·
LOL, Dr. Google again.
I get how it works—you type in one symptom and Google just serves up the absolute worst-case scenarios. It’s frustrating, I know. But honestly, I’m dealing with a few other things too, like tingling in my fingers, getting dizzy whenever I stand up (probably a blood pressure thing), and some unexplained weight loss... I'm kind of at a loss here. I feel like it has to be either a hematology issue or something neurological. Maybe it could be something like celiac disease, since my colonoscopy and GI tests didn't turn up anything specific.
brightgull95 brightgull95 Newcomer
7 messages
joined May 2022
#3792 ·
Someone on Google who apparently did their PhD in Germany—because over there, they slap that "Dr. med." title right in front of a doctor's name—what can you even say to that besides Aldar, bin begeistert..

Jokes aside, I don't deal with AL amyloidosis all that often. When it comes to ATTR, or the "wild type," the diagnosis is practically a given once certain markers hit, but even though ATTR seems to pop up more frequently than people realize, AL isn't exactly common either. Honestly, the current probability of you actually having that specific type is incredibly low, so if I were in your shoes, I wouldn't be losing any sleep over it. Even if some self-proclaimed "Dr. med." was pointing fingers at it.
Robert Davis9 Robert Davis9 Newcomer
8 messages
joined Mar 2023
#3793 ·
Thanks. I'll let you know what I decide after I talk to the hematologist. 😉
Jerry Ruiz5 Jerry Ruiz5 Newcomer
4 messages
joined Mar 2023
#3794 ·
I need some help regarding someone very close to me.

Female, 33 years old; 169cm, 57kg.
Has had Hashimoto since childhood and has been a rheumatology patient since 2018 (diagnoses include spondyloarthritis and suspected collagenosis).
She isn't on any long-term medication currently (she took Sulfasalazine but stopped), though she takes ibuprofen occasionally for pain.
Every evening, she runs a low-grade fever (her temperature jumps to 37-37.5C every single night).

Since June 2022, the left side of her ribs has been swollen (the skin over it looks flaky, like burst capillaries). A few weeks later, a lymph node on the left side of her neck, just below the jaw, swelled up—it’s been swollen constantly for months now, and it doesn't hurt when touched.
Since January 2023, lymph nodes in her groin have also started swelling.
Extreme night sweats, constant leg cramps (she takes magnesium daily, but it doesn't help), and her whole body is constantly itchy (mostly her legs, where white patches occasionally appear that itch terribly; there are no other rashes).
In the last four weeks, a brown spot appeared over the swollen lymph node on her neck, and she says she feels pressure (like she's overly full) when lying on her back. She has pain under her right shoulder blade and in her lower right abdomen. She’s complaining of constant bloating, fatigue, and terrible hair loss.

Today, the doctor finally sent her for blood and urine tests:
Test // Result // Ref. interval
Urea = 8.6 mmol/L , [2.8-2.3]
(S) ALP = 40 U/L , [54-119]

*I'm including this because I'm not sure if it matters, as they are hovering near the borderline values:
Lymphocytes 43.6 , [20-46]
At 138 mmol/L , [137-146]
Her TSH has risen from 1.8 to 2.47 since her last thyroid checkup last year.

URINE:
Bacteria = high
Epithelial cells 11-20 , [0-1(x400)]

She received a referral for a thyroid and neck ultrasound (it mentions A03 next to it).
I want to know if there is any way to fast-track this or get priority—does that kind of urgent referral even exist?
Which hospital in a major US city would you recommend we try?
I'm panicking for her. She's had a daily fever for months and now there's a brown spot over the swollen node.

Mods, please don't delete this if I did something wrong; I'll fix it. I know wait times can be months, but what if it's something malignant and she needs a biopsy?

Any advice is welcome, whether it's regarding the labs, specific exams, or which specialists we should see next.
DMs are open too.
Her cousin passed away at 32 from very aggressive breast cancer; one uncle had colon cancer and another had liver cancer. On her father's side, there was a death from vasculitis affecting the kidneys and lungs.
How can we speed this up?
George Johnson3 George Johnson3 Newcomer
1 message
joined Mar 2023
#3795 ·
Hey everyone... my dad is 63, and during a routine checkup on January 17th, they found out his blood sugar was through the roof, way over 22. He’s been kept in for observation and running all sorts of tests because the doctors initially suspected pancreatic cancer, but then the CT scan threw a curveball: the pancreas looks fine, but they spotted two different growths in his lungs. According to the CT, one smaller lesion is just a hamartoma, but the other one is "spicular" and measures about 3.4 cm... so they suspect a tumor. They did a bronchoscopy biopsy, which came back negative for cancer cells, and then they biopsied the lesion itself, which also came back negative for malignant cells. After that, he had a PET-CT scan, and here is the diagnosis:

Preliminary diagnosis and clinical question
Left lung lobe infiltration, Diabetes mellitus, referred by Dr. Janevski for diagnostic confirmation and staging
PET Scan
6.7 mmol/L
Findings
Tomograms were performed from the base of the skull down to the proximal parts of the thighs.
A low-dose CT was also conducted to correct attenuation and anatomical localization of the metabolically active changes.
No pathological uptake of the radiopharmaceutical was seen in the cervical, axillary, or mediastinal lymph nodes.
Pathological radiopharmaceutical uptake is visible in the consolidation of the left upper lung lobe, centrally translucent, measuring 1.9x1.4
cm (SUV max 6.32). Increased radiopharmaceutical uptake is also seen in a nodule in the right lower lung lobe (SUV max 2). In
the remaining lung parenchyma, there is no pathological uptake of the radiopharmaceutical.
Radiopharmaceutical uptake is noted in a formation in the left adrenal gland (SUV max 5.46), with an intensity similar to the uptake in the liver
parenchyma (SUV max 5.86), which aligns with the CT from early 2023 where this formation was characterized as an adenoma.
No pathological uptake of the radiopharmaceutical was observed in the abdominal, pelvic, or inguinal lymph nodes.
Diffuse, intense radiopharmaceutical uptake is visible in the intestinal loops, which makes analysis difficult—this is likely a side effect of metformin therapy.
An endoscopic exam should be performed if clinically indicated.
No pathological uptake of the radiopharmaceutical was detected in the visualized parts of the skeletal system.
Impression
Pathological glucose analog metabolism in the consolidation of the left upper lung lobe.
Metabolically active nodule in the right lower lung lobe. So what does this actually mean in the end? Is it some kind of carcinoma, or just inflammation? Honestly, we’re totally lost now. 🤔
Angela Wright Angela Wright Regular
731 messages
joined Feb 2007
#3796 ·
George Johnson3 said:Hey everyone... my dad is 63 and during a checkup on January 17th, they found his blood sugar was off the charts, over 22. He’s been hospitalized to run all the tests because the doctors were worried about pancreatic cancer. However, the CT scan showed something else entirely: the pancreas looks fine, but they found two masses in the lungs. According to the CT, one smaller lesion is a hamartoma, but the second one is "spiculated" and measures 3.4 cm... they suspect a tumor. They did a bronchoscopy biopsy, which came back negative for cancer cells, and then they biopsied the lesion itself, which also came back negative. They followed up with a PET-CT scan, and here is the diagnosis:

Indications and clinical question

Left lung upper lobe infiltration, Diabetes mellitus, referred by Dr. Janevski for diagnostic staging and definitive diagnosis

PET Scan

6.7 mmol/L

Findings

Tomograms were performed from the base of the skull to the proximal parts of the thighs.

A low-dose CT was also performed to correct attenuation and anatomical localization of metabolically active changes.

No pathological uptake of the radiopharmaceutical was observed in the cervical, axillary, or mediastinal lymph nodes.

Pathological uptake of the radiopharmaceutical is seen in the consolidation of the left lung upper lobe, centrally transparent, measuring 1.9x1.4

cm (SUV max 6.32). Increased uptake is also seen in a nodule in the right lung lower lobe (SUV max 2). In

the remaining lung parenchyma, there is no pathological uptake of the radiopharmaceutical.

Radiopharmaceutical uptake is noted in a formation in the left adrenal gland (SUV max 5.46), with intensity similar to that seen in the liver

parenchyma (SUV max 5.86), which is consistent with a CT scan from early 2023 where the formation was characterized as an adenoma.

No pathological uptake of the radiopharmaceutical was found in the abdominal, pelvic, or inguinal lymph nodes.

Diffuse intensive uptake of the radiopharmaceutical is visible in the intestinal loops, making analysis difficult; this is a result of Metformin therapy.

Perform an endoscopic exam if clinically indicated.

No pathological uptake of the radiopharmaceutical was seen in the visualized portions of the skeletal system.

Opinion

Pathological glucose analog metabolism in the left lung upper lobe consolidation.

Increased metabolically active nodule in the right lung lower lobe. So what is it in the end? Some kind of carcinoma, inflammation... now we just don't know anything anymore.🤔

I'm not sure where your father is receiving treatment, but I would recommend the Mayo Clinic. They deal with a massive variety of pathologies related to high blood sugar and will be able to pin down the situation very quickly.

Sent from my SM-G960F using Reddit
brightgull95 brightgull95 Newcomer
7 messages
joined May 2022
#3797 ·
George Johnson3 said:... so what is it in the end? Some kind of cancer, inflammation... now we just don't know anything anymore 🤔

This PET-CT report falls squarely into that category that certain clinicians—at least some of them—call "beating around the bush" or "it’s colder than it looks." There is a massive amount of text here, yet absolutely nothing definitive. Those spicules? They are certainly suspicious for something malignant, but if you actually trust the biopsy, then all those doubts have been wiped away. A localized inflammation—which is what the biopsy supposedly indicates regarding this issue—could definitely look exactly like what was described, but it won't just sit there forever. At this point, the only reasonable recommendation is to schedule another low-dose chest CT in about 3 to 6 months. And then, we just have to pray that whoever reads it actually knows what they're looking at. They say hope dies last, I suppose.
Nicholas Myers Nicholas Myers Active Member
163 messages
joined Jan 2012
#3798 ·
Jerry Ruiz5 said:Please help. This concerns someone very close to me.

Ma'am,

If a primary care physician suspects lymphoma—which seems to be the implication here—they can issue an urgent referral to a hematologist. That usually fast-tracks the patient for an immediate consultation and diagnostic workup.

The alternative is for the individual to head to the Emergency Room. They will be evaluated there and then directed toward the necessary follow-up testing.
Jerry Ruiz5 Jerry Ruiz5 Newcomer
4 messages
joined Mar 2023
#3799 ·
Maria Fisher46 said:Ma'am,

If a family doctor suspects lymphoma—which is how you phrased this—there should be an option for a priority referral to a hematologist so the patient can be seen and processed quickly.

The other option is just heading straight to the ER to get evaluated and sent for further testing.

I don't get it. If this has been going on for months and clearly getting worse, why isn't there a priority referral?
Does anyone know why that is?
That’s what's bothering me. I know they used to issue those referrals, but has something changed recently?

Since 2018, my kid has dealt with all sorts of symptoms: low-grade fevers at night, pain, balance issues (an MRI showed a cyst on the epiphysis, but they claimed it was irrelevant—but what if the reading was wrong?), swollen lymph nodes, and constant vomiting. She's tested positive for ANA antibodies and some other things I can't even recall right now, yet according to their latest blood test, everything is supposedly "fine."
My child is wasting away while they tell us to wait until the blood work looks bad enough for them to actually notice something.
Thanks for any advice.
If anyone thinks of anything else, please let me know.
Nicholas Myers Nicholas Myers Active Member
163 messages
joined Jan 2012
#3800 ·
Jerry Ruiz5 said:I don't get it. We're looking at something that has been dragging on for months and clearly worsening, yet this referral doesn't look right.
Does anyone know why?
That’s what’s bothering me. I know they used to issue referrals like this, but I'm not sure if the rules have changed recently.

The patient has been dealing with various symptoms since 2018—low-grade fevers in the evening, pain, balance issues (an MRI showed a lesion on the epiphysis, which they claimed was irrelevant, but what if the reading was wrong?). Lymph nodes are swollen, constant nausea, positive ANA antibodies, and a few other things I can't quite recall right now. Despite all this, according to the latest blood test results, everything supposedly looks normal.
The patient is deteriorating, yet they're being told to wait until the lab work gets "bad enough" for doctors to actually take notice.
Thanks for any advice.
If anyone thinks of anything else, please let me know.

Based on your description, which is somewhat muddled, the timeline of these symptoms isn't clear. You mention 2018, yet previously you cited January 2023. It stands to reason that if the issues began back in 2018, a priority referral wouldn't be issued—especially if the patient has already been under medical care for these specific symptoms. In those cases, the standard procedure is a second opinion referral.

There are several ambiguities here. Furthermore, a 33-year-old is an adult, not a child.

You must log in or register to reply here.

Log in Register

🔗 Similar threads