CheckEmoji Community · the emoji forum
🏠 Home 🆕 What's new ❓ Unanswered 🔥 Popular 📡 RSS Members 👥 0 online log in · register
Home › Lifestyle › Health › Lab results - looking for opinions [PLEASE READ 1ST POST]

Lab results - looking for opinions [PLEASE READ 1ST POST]

Started by vividsailor7 · · 👁 51 views · 3.9K replies

📡 Subscribe to replies

Participants vividsailor7redcrane22Sandra Rivera37swiftbear86melloworca6Dana Martin87ironskipper80mellowgardener15goldenmarlin6analogbison13Nicholas Myersstormygardener34Roger RodriguezDonna Mitchell3Kenneth Vaughn2Laura Ward98briskseal32Susan Vaughn46Zachary Lewis4driftingmason52rustyheron55Laura Chavez47vividstag24lonecanyon8 …
Nicholas Myers Nicholas Myers Active Member
163 messages
joined Jan 2012
#3521 ·
Rachel Davis said:They sent me in for a urine culture because my white blood cell count was up and they found bacteria in my urine, but I can't make sense of this report:
leukocytes positive (~15), erythrocytes and nitrites negative. Microorganism count 10^4 CFU/ml. Resident flora of the distal urethra.

There are no signs of a urinary tract infection.
Peter Rogers Peter Rogers Active Member
60 messages
joined Dec 2011
#3522 ·
Maria Fisher46 said:Hi there,

I’d suggest running some extra tests just to be safe: anti-dsDNA, anti-SS-A, CH50, LAC, beta-2-GPI, IgM and IgG anticardiolipin antibodies, ANCA, serum protein electrophoresis, urine albumin/creatinine ratio, CK, PV, APTV, fibrinogen, D-dimers, bilirubin, Na, K, Cl, Ca, Mg, P, a peripheral blood smear, three stool tests for occult bleeding and calprotectin, an abdominal ultrasound, chest X-ray, and an echocardiogram. Combine those with what you've already done, and then maybe some more depending on how the symptoms play out. Also, check serology for EBV, CMV, bartonella, and a QuantiFERON test.

Thanks so much!
That list you suggested seems pretty massive to me.
We’re still stuck waiting for even a chance to actually sit down with an immunologist, so we’ll just have to see what happens. Given how much ground you're covering with these tests, do you think there are specific things we should prioritize or really push for if needed?
Unfortunately, our experience here in the States is that doctors tend to take a much more "minimalist" approach to situations like this.
If we hit a wall, could you recommend a place where we might actually get this kind of thorough workup?
It doesn't matter if it's in Washington, D.C.; pretty much all of our other kid's doctors are based in Washington, D.C. anyway.
Nicholas Myers Nicholas Myers Active Member
163 messages
joined Jan 2012
#3523 ·
Emily Ortiz27 said:Thank you so much!
What you're recommending seems quite extensive.
We're still waiting for an opening to even see an immunologist, so we'll have to see what's possible. Given how broad this testing panel is, do you think there are specific areas we should focus on or push for if needed?
Unfortunately, our experience here is that these kinds of situations are handled much more modestly.
If things don't work out, could you suggest a place where we might get this level of diagnostic work done?
It doesn't matter if it's in Washington, D.C.; almost all of the doctors for my other child are based in Washington, D.C. anyway.

Ma'am,

if the child is still running a fever, I believe all those tests are necessary. It's a different story if the fever has subsided.

If you can't get these tests done locally, regarding a child with these specific issues, you can make an appointment at the pediatric rheumatology clinic at Children's Hospital.
Peter Rogers Peter Rogers Active Member
60 messages
joined Dec 2011
#3524 ·
Maria Fisher46 said:Hi there,

if the kid is still running a fever, I’d say you definitely need all those tests we talked about. It's a different story if the fever has already broken.

If you can't get those specific labs done where you are, you should probably just book an appointment at the pediatric rheumatology clinic over at Children's Hospital in Chicago.

Thank you so much.
Instead of going through the usual follow-up with the immunologist, I actually found a report online on a health portal that was issued for my daughter.

image

The thing is, this report—aside from being handed out without any actual communication or a proper physical exam—is completely different from what you suggested. So, how do I even handle this? What’s the move here?
Should I take this report and go looking for a second opinion at Children's Hospital in Chicago?
She currently has an active referral for the post-COVID clinic in Miami, so I have no clue if I can even use another referral to see a specialist at a different institution.
And who am I even supposed to talk to once I get to the hospital in Chicago?
My girl isn't running a fever every single day anymore; sometimes her temp is totally fine, sometimes it hits 98.6, and other times it spikes higher.
But that abdominal pain? It hasn't gone away, and it seems to flare up even more when she's moving around.
Also, what's the deal with sports? She trains three times a week, plus she's pretty consistent with her PE classes back at school.
brightscout9 brightscout9 Newcomer
4 messages
joined Dec 2021
#3525 ·
Hey everyone,

I just went back and pulled my lab results from about four months ago...

Would love to get some thoughts on this...

Thanks.

https://amaranth-dorris-41.tiiny.site/
Carl Thompson26 Carl Thompson26 Newcomer
4 messages
joined Apr 2022
#3526 ·
Dear all,

I would appreciate your insights regarding my recent lab work. I am a 36-year-old male, otherwise healthy, fully vaccinated (two doses), and have never contracted COVID-19. I had my first blood panel performed in January, and the results were as follows:

WBC 2.7
NEUTROPHIL GR 1.60
MONOCYTES 0.30

These findings were repeated in the second and third months, showing similar consistency.

April 14, 2022
CYTOLOGY REPORT RESULTS:

eosinophilic granulocytes 1%
segmented neutrophil granulocytes 54%
lymphocytes 31%
reactive lymphocytes 10%
monocytes 4%

RBC: mild anisopoikilocytosis, normochromia
WBC: normal morphology
PLT: present, normal morphology

The recommendation provided was a full hematological evaluation.
Nicholas Myers Nicholas Myers Active Member
163 messages
joined Jan 2012
#3527 ·
Quote : EL Gato Félix
Emily Ortiz27 said:Thank you. Much appreciated.
Instead of waiting for an actual follow-up appointment with the immunologist, I stumbled upon the girl's lab results on a health portal.

image

This report was issued without any follow-up communication or a proper clinical review of my child. On top of that, the findings completely contradict the guidelines you provided. How do you suggest I proceed from here?
Should I just stick with the results, or reach out for a second opinion at Mayo Clinic?
I currently have an active referral for the post-COVID clinic in Miami, so I’m not entirely sure if I could even use a different referral to see the same specialist at another facility.
And who exactly should I contact over in Miami?
The little girl isn't running a fever every single day anymore. It fluctuates—sometimes she’s back to normal, sometimes it hits 98.6°F, and other times it creeps up a bit higher.
Abdominal pain persists. It’s more pronounced following physical activity.
How should we approach physical activity here? He’s training three times a week, and that doesn't even account for his regular PE classes at school.

Dear Madam,

I wrote my initial assessment based on the specific history provided: a young girl referred to a post-COVID clinic following prolonged fever, where she underwent an immunology consultation. My response was simply outlining the necessary diagnostic steps for anyone presenting with persistent fever and the specific lab results you shared.

Now that the fever has broken, my answer to that question would look quite different.

One fact remains, though: the reasoning behind ordering an ANA test. If the girl didn't have a fever at the time she saw the immunologist, the motivation for that specific lab work is unclear. It’s a well-documented phenomenon that ANA titers can spike—sometimes even reaching high levels—months after a SARS-CoV-2 infection or other viral bouts, such as mononucleosis. But you don't just run an ANA for those conditions. You order it when there is actual clinical suspicion of systemic connective tissue diseases, like lupus, lupus-related disorders, or certain autoimmune liver issues. In almost any other scenario, the test provides zero value for diagnosis or prognosis. To be blunt, it's an unnecessary expense. I fail to see why the immunologist felt this test was warranted.

Now that the test results are in—results that show a deviation—I have to wonder: which clinician looked at the clinical picture, factored in the history of a prior SARS-CoV-2 infection, and arrived at a conclusion that actually made sense? I’m circling back to my original question: what role did the ANA play in this entire diagnostic process? Why was it ordered in the first place, and how exactly did it guide the physician toward their final conclusion? I’d be interested to hear some actual reasoning on that.

Second, I have to disagree with how they handled the data—or rather, the lack of action regarding it. Specifically, the note that "abdominal pain persists and intensifies with movement." So, we have a child reporting stomach pains, yet no abdominal ultrasound was even requested? Honestly, I can't wrap my head around why.

Since things seem to be settling down and resolving on their own, most of those tests I mentioned earlier probably aren't strictly necessary. That said, if the abdominal pain persists, I’d suggest getting an abdominal ultrasound just to be safe.

Blood cultures probably aren't worth the effort at this stage. However, if that abdominal pain persists, I’d still suggest running a serum protein electrophoresis, checking the albumin/creatinine ratio from a urine sample, testing stool for occult blood three times, getting a calprotectin test, and scheduling an abdominal ultrasound. Ultimately, though, my decision would hinge on the physical exam and the clinical picture.
Nicholas Myers Nicholas Myers Active Member
163 messages
joined Jan 2012
#3528 ·
brightscout9 said:To whom it may concern,

Ponovi sam nalaze koje sam radio prije cca 4 mjeseci

I'd appreciate your thoughts on this...

Thanks.

https://amaranth-dorris-41.tiiny.site/

To whom it may concern,

Transferin saturation remains high at 75%, even with the recent spike in creatine kinase. Given these results, it’s time to touch base with the primary care physician to figure out the next steps for testing.
Nicholas Myers Nicholas Myers Active Member
163 messages
joined Jan 2012
#3529 ·
Carl Thompson26 said:Hello,

I’d appreciate some insight. 36 years old, healthy, fully vaccinated (two doses), never had COVID. Had blood work done in January; results were:

WBC 2.7
NEUTROPHILS 1.60
MONOCYTES 0.30

Results repeated in February and March. They remain consistent.

April 14, 2022
DKS CYTOLOGY REPORT:

eosinophil granulocytes 1%
segmented neutrophil granulocytes 54%
lymphocytes 31%
reactive lymphocytes 10%
monocytes 4%

ER: mild anisopoikilocytosis, normochromia
GR: normal morphology
TR: present, normal morphology

Recommendation: hematological follow-up.

Hello,

From what I can see, you have lymphopenia, which warrants further investigation.

The first question is how your blood counts usually look—I assume you've had labs done at some point in your life. In other words, is this low white cell count a new development from January 2022, or have your levels always sat at the bottom end of the normal range? Have you been sick at all in the last six months? Is it possible you had an infection, a fever, or just felt unwell recently? Have you had any medical exams lately? Any high-risk sexual encounters? Are you taking any medications or consuming alcohol? What about your weight—has it shifted significantly in the last six months? Have you dealt with any serious infections? Fevers, night sweats? Rashes or skin changes?
Peter Rogers Peter Rogers Active Member
60 messages
joined Dec 2011
#3530 ·
Maria Fisher46 said:Look, ma'am,

I was giving you my two cents based on the info I had at the time—which was basically, "this little girl was sent to a post-COVID clinic because she’s been running a fever for ages," followed by a consultation with an immunologist. I was simply outlining what needs to be done for someone dealing with prolonged fever and the specific lab results you laid out.

Now that the kid isn't even running a fever anymore, it's pretty obvious my answer to your question would look totally different today.

But we still have to deal with one glaring issue: the whole ANA testing thing. If the girl wasn't even febrile when she saw that immunologist, then why on earth was that test ordered in the first place? It's common knowledge that ANA can come back positive, even with high titers, months after a bout with COVID-19, or even after other infections like those causing mononucleosis syndrome. But you don't just go hunting for ANA in all those cases. You only pull that trigger if there's actual suspicion of systemic connective tissue diseases—think Lupus, related disorders, or autoimmune liver issues—plus a few other rare exceptions. In almost any other scenario, that test adds zero value to a diagnosis or prognosis, and frankly, it's unjustifiable. I honestly don't get the logic behind the immunologist requesting it.

So now that the results are in and they're abnormal, the doctor decided to draw a conclusion that seems perfectly logical just looking at her history of COVID-19. Which brings me back to my point: what role did the ANA actually play here? Why was it requested, and how did it specifically help that doctor reach their conclusion? I’d love to hear an actual answer to that.

Second off, I really can't wrap my head around the failure to act on the fact that "abdominal pains are still present and worse with movement." Seriously? The child is having stomach pains and nobody thought to order an abdominal ultrasound?! I truly cannot fathom that lack of follow-through.

Since things seem to be settling down and resolving on their own, maybe all those tests I mentioned before aren't strictly necessary, but in my book, if there's still abdominal pain, you should at least be doing an abdominal ultrasound.

Blood cultures probably don't make sense anymore. However, I still think a serum protein electrophoresis, a urine albumin/creatinine ratio, checking stool for occult blood three times, calprotectin, and an abdominal ultrasound are worth doing if that belly is still hurting—though, realistically, I'd base that call on a physical exam and clinical intuition.

Thank you so much.
I suppose the decision to run those tests was influenced by the fact that she still had a fever during the initial exam, but in the 5 or 6 weeks we've been waiting for results, her temperature has stabilized to somewhere between 98.2 and 99.0°F.
Based on your advice, we'll follow up with our family doctor to get those tests you recommended moving forward.
David Flores68 David Flores68 Newcomer
3 messages
joined Mar 2018
#3531 ·
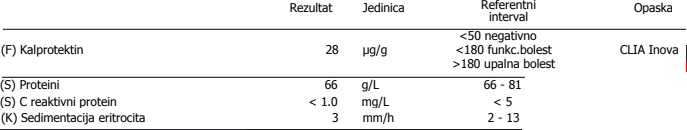
Could someone please help me interpret these results?

image

I’m a 33-year-old male. These tests were ordered because I've been developing these nodules on the fingers of my right hand—but I also have a history of undiagnosed gastrointestinal issues that have been hanging over me for years. I'm honestly not sure if my doctor requested this panel because of the skin symptoms or the gut problems.

As for the rest of the findings, they seem to fall within the standard reference ranges, though I wonder if they might still be hinting at something—perhaps ruling certain things out. Here they are:
imageupload photo
Brenda Parker5 Brenda Parker5 Active Member
59 messages
joined Aug 2020
#3532 ·
David Flores68 said:Can someone please help me make sense of these results?

image

I'm a 33-year-old guy—ordered these tests because I've been getting these weird bumps popping up on my right fingers, though I've also dealt with some undiagnosed GI issues for years now. Honestly, I can't tell if my doctor ordered this because of the skin stuff or the stomach trouble.

As far as I can tell, the rest of the numbers look normal, but maybe they're hinting at something—like maybe they rule certain things out—so here they are:
imageupload photo

Your Vitamin D is chronically low, and man, that causes a massive ripple effect—one of the biggest issues is that it automatically tanks your glutathione levels.
Start supplementing with 5000 IU of D3 paired with K2.
David Flores68 David Flores68 Newcomer
3 messages
joined Mar 2018
#3533 ·
Jacob Lopez51 said:You’re dealing with chronically low Vitamin D—which brings its own baggage—and one of the biggest fallout effects is an automatic drop in glutathione levels.
Just start supplementing with 5,000 units of D3 paired with K2.

Does this low Vitamin D level point toward anything regarding my gastrointestinal issues?

Can I just fix this by getting some sun instead of relying on supplements?
Nicholas Myers Nicholas Myers Active Member
163 messages
joined Jan 2012
#3534 ·
David Flores68 said:Could someone please help me interpret these results?

image

I'm 33. My doctor ordered this panel because of some nodules popping up on my right fingers, though I've been dealing with undiagnosed GI issues for years now. Honestly, I can't tell if she's looking into the first or the second.

As far as I can tell, these other results fall within the normal range. Still, they might be saying something significant—perhaps ruling certain things out. Here they are:
imageI can't see any images yet. Go ahead and upload the photo whenever you're ready.

To whom it may concern,

Normal calprotectin levels, paired with steady CRP and ESR readings, suggest that your GI issues likely aren't stemming from inflammatory bowel disease. That’s the takeaway from this specific set of data. However, it doesn't rule out other culprits; it just means we can't point to IBD as the cause based on these numbers alone.

Low vitamin D levels signal a deficiency that needs addressing with supplementation. Given how low these numbers can get, the most effective approach is typically a high-dose regimen—something like 50,000 units once a week for about six to eight weeks—before transitioning to a standard maintenance dose. In the US, you'd likely see a prescription for an oral solution like D-vital to get things back on track.

Regarding those nodules, this specific result doesn't point to a clear culprit just yet. One possibility could be calcium depletion stemming from a long-term Vitamin D deficiency—which might trigger secondary hyperparathyroidism—though that doesn't strike me as particularly likely in your situation. Still, once we review everything, it would be worth considering whether checking your calcium, PTH, and magnesium levels makes sense. Ultimately, a physical exam and a biopsy remain the gold standard for getting a definitive diagnosis.
Kenneth Harris68 Kenneth Harris68 Newcomer
3 messages
joined Jun 2020
#3535 ·
Hi there.

Can someone help me make sense of these blood test results? A few of the values are outside the normal range.

Thanks
Anthony Wood11 Anthony Wood11 Newcomer
3 messages
joined Dec 2012
#3536 ·
Greetings.
Could someone take a look at these blood results? I’m trying to determine if there’s actually cause for concern here.

https://ibb.co/PYLZjqC
https://ibb.co/8Nnc1z0

Edit: For context, I’m 38 years old, generally in good shape, and maintain a regular exercise routine. I haven't really been dealing with any glaring symptoms, though I have noticed a bit of fatigue creeping in during the afternoons over the last two weeks—though I suspect that's just the usual fallout from stress and a lack of sleep. As for my GGT, it’s been running slightly elevated for about five years now, consistently hovering somewhere between 73 and 83. Back when this started five years ago, my primary care physician in Washington, D.C. didn't think it was anything worth noting.
Maria Allen6 Maria Allen6 Newcomer
7 messages
joined May 2018
#3537 ·
Anthony Wood11 said:Best regards!
Could someone take a look at these blood work results and give me an analysis? Should I be worried about any of this?

https://ibb.co/PYLZjqC
https://ibb.co/8Nnc1z0

Edit: For context, I’m 38 years old, stay in pretty good shape, hit the gym regularly, and haven't noticed any major symptoms—just been feeling a bit drained in the afternoons over the last couple of weeks, though I suspect that's just a byproduct of stress and not getting enough sleep lately. Also, my GGT has been running high like this for about five years now, usually hovering somewhere between the 73 and 83 range. Back then, my primary care physician at the local clinic didn't think much of it.

What are you even on about? Alcohol and sugar are what drive those GGT numbers up, and if you ask me, sugar is the real silent killer here. Cut out the sugar for two or three months and I guarantee you'll see those levels drop back into the normal range. As for the lipids, honestly, I find it hard to believe anyone actually keeps their triglycerides and cholesterol within the standard limits these days. Your kidney markers are slightly elevated, but it doesn't look like anything to sweat over.
Anthony Wood11 Anthony Wood11 Newcomer
3 messages
joined Dec 2012
#3538 ·
Raymond Smith53 said:What are you even chirping about? GGT is just reacting to alcohol and sugar intake. Sugar is the true villain here. Cut out the sweets for two or three months and I guarantee those numbers will stabilize. As for lipids—honestly, I doubt anyone actually has their triglycerides and cholesterol within a healthy range. A slight elevation in kidney markers isn't even worth worrying about.

I’m hardly a heavy drinker; it's more of an occasional thing, maybe once or twice a month. And sugar? I barely touch it. There are stretches of months where I won't eat a single sweet thing. I stay quite disciplined with my diet and hit the gym regularly. My body mass hasn't really budged in over ten years—give or take a pound or two.
Frank Anderson9 Frank Anderson9 Newcomer
8 messages
joined Jun 2022
#3539 ·
Hey everyone,
My wife’s mom has been having a rough two weeks. She’s running a constant fever, usually hitting 100.4°F or 101°F. She’s had blood work done three times now, and the results aren't looking great. She’s been on antibiotics for seven days straight, but there hasn't been any real improvement—aside from some movement in her urinalysis.
Latest values: CRP 236
WBC 19
Platelets 663
Hemoglobin 113
Neutrophils 83 and 16
Monocytes 1.2
Iron 2

Urinalysis:
RBC/Hemoglobin 2+ (was 3+ before the antibiotics)
Bacteria rare (were frequent before)
WBC 1-3, was previously 2-5
RBC up to 10, was up to 15.
Previously, her urobilinogen was 2+, but that's normal now. Leukocyte esterase was 1+ but is okay now too. She also had borderline positive protein and other stuff, but everything looks fine on the latest report.
Liver/Enzymes:
ALT 125
AST 69
GGT 227
ALP 296

She had an abdominal ultrasound, which came back clear, and they scanned her lungs and heart—all good there. The doctor did a full exam; she doesn't have any specific pain, just extreme weakness, and she’s barely eating anything at all.

For context, she’s been under massive stress for a long time and could be described as being in a pre-depressive state.

We’re seriously worried because, aside from the urine markers, her condition hasn't improved with the antibiotics at all. In fact, things seem to be getting worse (her last CRP was 184).

Any thoughts? We’re terrified it might be something malignant, though the doctor says the labs don't point in that direction.

Thanks!
Nicholas Myers Nicholas Myers Active Member
163 messages
joined Jan 2012
#3540 ·
Frank Anderson9 said:Hi everyone,
my wife's mother has been doing poorly for two weeks now.

To whom it may concern,

Was this procedure ordered based on a recommendation from her primary care physician?

Given these results and how long she's been suffering, hospitalization seems necessary.

You must log in or register to reply here.

Log in Register

🔗 Similar threads